


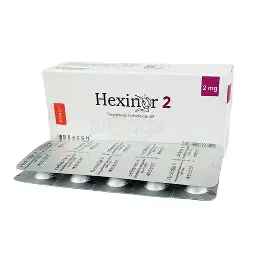
Hexinor 2-MG Tablet
Made in:
Brand:
Capacity:

Authentic Product

Easy Return

Secure payments and fast deliveries
Indications Hexinor tablet is indicated as an adjunct in the treatment of all forms of parkinsonism (postencephalitic, arteriosclerotic, and idiopathic). It is often useful as adjuvant […]
Indications
Pharmacology
Dosage & Administration
Dosage should be individualized. The initial dose should be low and then increased gradually, especially in patients over 60 years of age. Whether Trihexyphenidyl may best be given before or after meals should be determined by the way the patient reacts. Postencephalitic patients, who are usually more prone to excessive salivation, may prefer to take it after meals and may, in addition, require small amounts of atropine which, under such circumstances, is sometimes an effective adjuvant. If Trihexyphenidyl tends to dry the mouth excessively, it may be better to take it before meals, unless it causes nausea. If taken after meals, the thirst sometimes induced can be allayed by mint candies, chewing gum or water. Abrupt withdrawal of treatment for Parkinsonism may result in acute exacerbation of Parkinsonism symptoms; therefore, abrupt withdrawal should be avoided. Abrupt withdrawal of treatment may result in neuroleptic malignant syndrome (NMS).
Idiopathic Parkinsonism: As initial therapy for parkinsonism, 1 mg of Trihexyphenidyl form may be administered the first day. The dose may then be increased by 2 mg increments at intervals of three to five days, until a total of 6 to 10 mg is given daily. The total daily dose will depend upon what is found to be the optimal level. Many patients derive maximum benefit from this daily total of 6 to 10 mg, but some patients, chiefly those in the postencephalitic group, may require a total daily dose of 12 to 15 mg.
Drug-Induced Parkinsonism: The size and frequency of the Trihexyphenidyl dose needed to control extrapyramidal reactions to commonly employed tranquilizers, notably the phenothiazines, thioxanthenes, and butyrophenones, must be determined empirically. The total daily dosage usually ranges between 5 and 15 mg although, in some cases, these reactions have been satisfactorily controlled with as little as 1 mg daily. It may be advisable to commence therapy with a single 1mg dose. If the extrapyramidal manifestations are not controlled in a few hours, the subsequent doses may be progressively increased until satisfactory control is achieved. Satisfactory control may sometimes be more rapidly achieved by temporarily reducing the dosage of the tranquilizer when instituting Trihexyphenidyl therapy and then adjusting the dosage of both drugs until the desired ataractic effect is retained without onset of extrapyramidal reactions. It is sometimes possible to maintain the patient on a reduced Trihexyphenidyl dosage after the reactions have remained under control for several days. Instances have been reported in which these reactions have remained in remission for long periods after Trihexyphenidyl therapy was discontinued.
Concomitant use with Levodopa: When Trihexyphenidyl is used concomitantly with levodopa, the usual dose of each may need to be reduced. Careful adjustment is necessary, depending on side effects and degree of symptom control. Trihexyphenidyl dosage of 3 to 6mg daily, in divided doses, is usually adequate. Concomitant use with other Parasympathetic Inhibitors: Trihexyphenidyl may be substituted, in whole or in part, for other parasympathetic inhibitors. The usual technique is partial substitution initially, with progressive reduction in the other medication as the dose of Trihexyphenidyl is increased.
The total daily intake of Trihexyphenidyl tablet is tolerated best if divided into 3 doses and taken at mealtimes. High doses (>10 mg daily) may be divided into 4 parts, with 3 doses administered at mealtimes and the fourth at bedtime.
Use in children: Safety and effectiveness in pediatric patients have not been established.
Interaction
Contraindications
Side Effects
Pregnancy & Lactation
Precautions & Warnings
evidence of anhidrosis, the possibility of hyperthermia should be considered. Dosage should be decreased so that the ability to maintain body heat equilibrium via perspiration is not impaired. Severe anhidrosis and fatal hyperthermia have occurred with the use of anticholinergics under the conditions described above. Neuroleptic Malignant Syndrome: A potentially fatal symptom complex sometimes referred to as Neuroleptic Malignant Syndrome (NMS) has been reported in association with dose reduction or discontinuation of Hexinor. Clinical manifestations of NMS are hyperpyrexia, muscle rigidity, altered mental status and evidence of autonomic instability (irregular pulse or blood pressure, tachycardia, diaphoresis and cardiac dysrhythmias).
Overdose Effects
In humans, doses up to 300 mg (5 mg/kg) have been ingested without fatalities or sequelae. However, rare cases of death associated with Hexinor over dosages taken in conjunction with other CNS-depressant agents have been reported or in patients with a compromised respiratory condition. Hexinor blood concentrations associated with the fatalities ranged from 0.03 to 0.80 mg/I.
Signs and Symptoms: Over dosage with Hexinor produces typical central symptoms of atropine intoxication (the central anticholinergic syndrome). Correct diagnosis depends upon recognition of the peripheral signs of parasympathetic blockade, including dilated and sluggish pupils; warm, dry skin; facial flushing; decreased secretions of the mouth, pharynx, nose, and bronchi; foul-smelling breath; elevated temperature; tachycardia, cardiac arrhythmias; decreased bowel sounds; and urinary retention. Neuropsychiatric signs such as delirium, disorientation, anxiety, hallucinations, illusions, confusion, incoherence, agitation, hyperactivity, ataxia, lip smacking and tasting movements, loss of memory, paranoia, combativeness, and seizures may be present. The condition can progress to stupor, coma, paralysis, cardiac and respiratory arrest, and death.
Treatment: Treatment of acute overdose involves symptomatic and supportive therapy. Gastric lavage or other methods to limit absorption should be instituted. A small dose of diazepam or a short-acting barbiturate may be administered if CNS excitation is observed. Phenothiazines are contra-indicated because the toxicity may be intensified due to their antimuscarinic action, causing coma. Respiratory support, artificial respiration or vasopressor agents may be necessary. Hyperpyrexia must be reversed, fluid volume replaced and acid-balance maintained. Urinary catheterization may be necessary. It is not known if Hexinor is dialyzable.
Therapeutic Class
Storage Conditions
| Capacity | 10 Tablets ( 1Strips ) |
|---|
Related products
- Capacity: 10 Tablets (1 Strip)
৳ 125.00
- Capacity: 10 Tablets (1 Strip)
৳ 80.00
- Capacity: 10 Tablets (1 Strip)
৳ 350.00
- Capacity: 10 Tablets (1 Strip)
৳ 500.00
- Capacity: 10 Tablets (1 Strip)
৳ 200.00


Reviews
There are no reviews yet.